Blood tests: Doctors may measure troponin, a protein released into the blood when heart muscle cells are injured. Elevated troponin can indicate heart muscle damage, but it does not identify the cause by itself. Other blood tests may look for inflammation or help assess alternative diagnoses.
Echocardiogram: This is an ultrasound examination of the heart. It allows clinicians to assess the heart's structure, pumping function, and movement of its walls. It can help identify complications, although some people with myocarditis have a relatively normal echocardiogram.
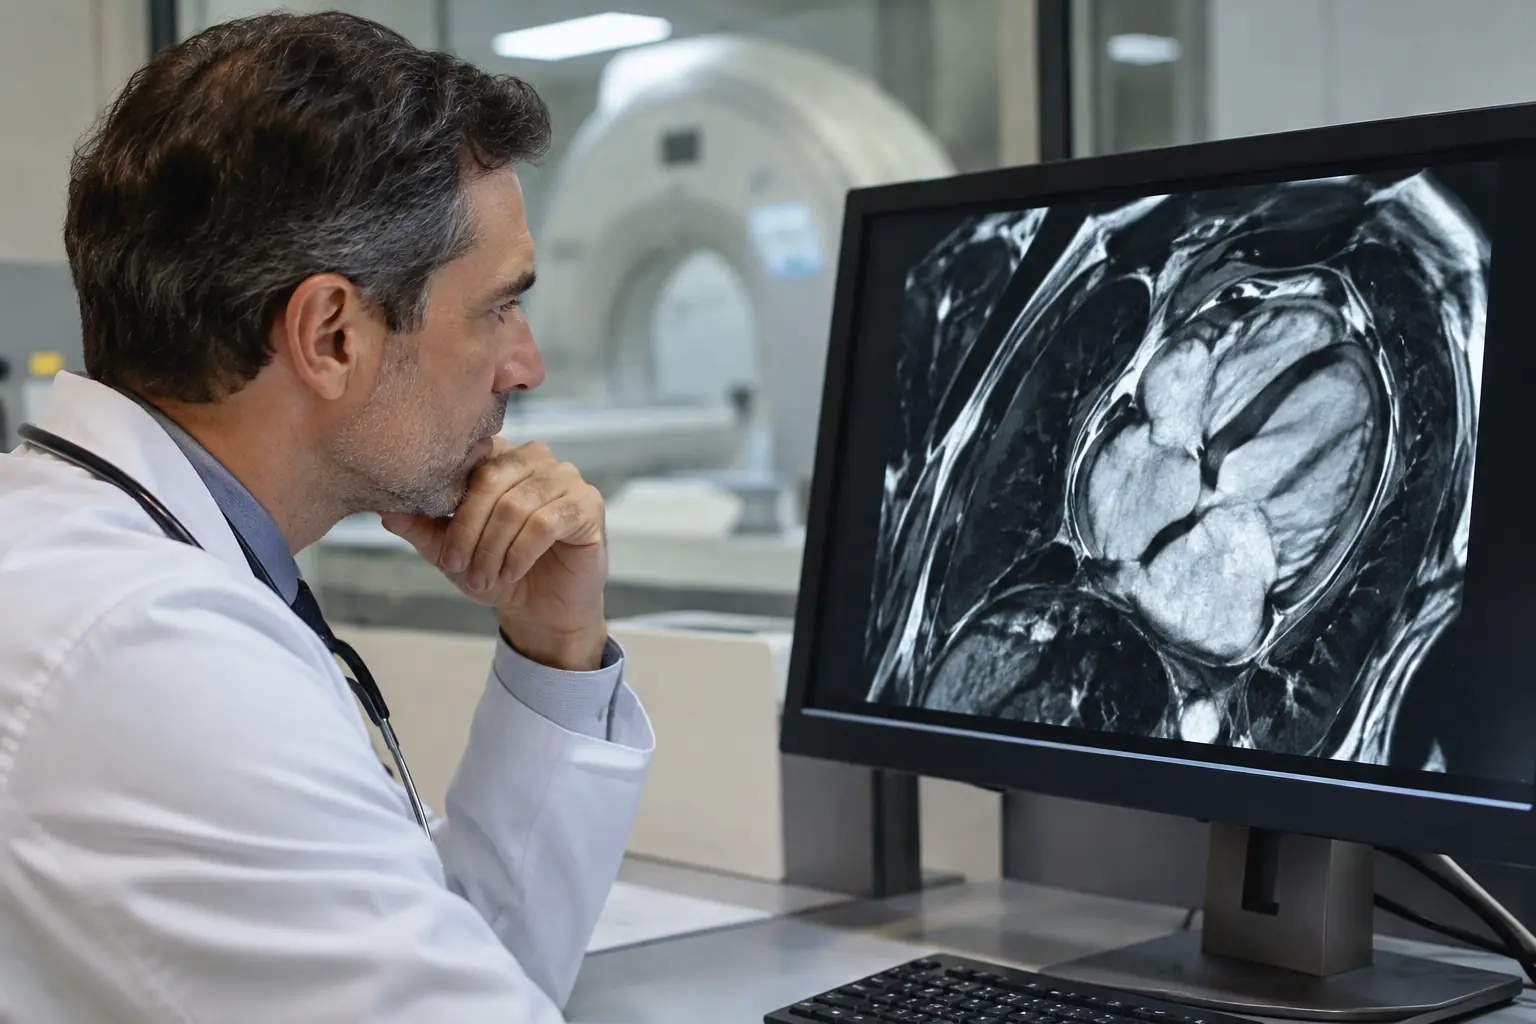
Cardiac magnetic resonance imaging (MRI): Cardiac MRI can provide detailed information about heart muscle inflammation and injury. It is an important tool in evaluating suspected myocarditis and may be used when the diagnosis remains uncertain or when more detailed assessment is needed.
Additional investigations: Depending on the person's condition, doctors may consider chest imaging, monitoring of heart rhythm, or other tests to investigate alternative causes and complications.
No single test should be interpreted in isolation. A clinician considers the results together with symptoms, examination findings, and the person's medical history.
Why the X-ray in the supplied image does not prove myocarditis
The screenshot displays three full-body X-ray images, alongside a small graphic of a syringe and vaccine vial. The accompanying text discusses myocarditis. However, the image itself does not show evidence that the people pictured developed myocarditis, and it does not establish a connection between those X-rays and COVID-19 vaccination.
A conventional chest X-ray can help doctors look for certain lung or heart-related changes, but it is not a definitive test for inflammation of the heart muscle. Myocarditis is generally assessed through clinical findings, ECG, blood tests, echocardiography, and, when appropriate, cardiac MRI.
Readers should be particularly cautious when an online article places dramatic medical images next to a vaccine headline without identifying the patients, explaining the diagnosis, or providing the original clinical source.
An image can attract attention, but it cannot replace medical evidence.
8. Does Myocarditis Always Cause Permanent Heart Damage?
No. Myocarditis does not always lead to permanent heart damage.
Many cases, including many reported after mRNA COVID-19 vaccination, have had a relatively mild short-term clinical course. Some patients improve with medical care, monitoring, and temporary restrictions on physical activity.
However, it would also be inaccurate to claim that every case resolves completely or that there is never a longer-term concern.
The FDA's June 2025 safety communication discussed follow-up information from a study of people diagnosed with myocarditis after receiving an mRNA COVID-19 vaccine. At a median follow-up of approximately five months, abnormal findings on cardiac MRI that can indicate previous heart muscle injury remained common. Some people also reported cardiac symptoms around three months after diagnosis.
The FDA emphasized that the clinical and prognostic significance of those MRI findings is not yet known. In other words, an imaging abnormality may remain visible, but researchers do not yet know precisely what it means for every patient's long-term health.
This is an important point because online discussions sometimes make two opposite claims.
One side may suggest that all vaccine-associated myocarditis is harmless and disappears immediately. The other may claim that every case causes permanent heart damage. Neither statement accurately reflects the available evidence.
Recovery depends on the severity of inflammation, the individual's overall health, the presence of complications, and the results of follow-up assessments.
People diagnosed with myocarditis should follow the advice of their treating clinician. They should not assume that feeling better means they can immediately return to strenuous exercise or competitive sport.
9. Why Exercise May Need to Be Restricted During Recovery
Physical activity is generally beneficial for heart health. Regular movement can improve cardiovascular fitness, help control blood pressure, and support overall well-being.
But myocarditis is an exception to the idea that more exercise is always better.
When the heart muscle is inflamed, strenuous activity can place additional demands on an organ that may not yet have recovered. Depending on the condition, exercise may increase the risk of abnormal heart rhythms or other complications.
For this reason, people diagnosed with myocarditis are commonly advised to avoid strenuous exercise during the recovery period. The length of restriction and the timing of a return to activity should be determined by a medical professional based on symptoms, test results, and follow-up evaluation.
This is particularly relevant for young people who participate in competitive sports, intense gym training, running, or physically demanding work.
A person should not decide independently to resume intense exercise simply because chest discomfort has disappeared. Recovery may need to be assessed through clinical review and, in some cases, repeat testing.
The same caution applies to people who suspect they may have myocarditis but have not yet been examined. New chest pain, breathlessness, or palpitations should be evaluated rather than tested through a workout.
The goal is not to make people afraid of exercise. It is to protect the heart while inflammation is being assessed and treated.
10. Is COVID-19 Infection Also a Risk to the Heart?
Yes. COVID-19 infection itself can affect the cardiovascular system.
The virus and the body's response to infection can contribute to inflammation, blood clotting, damage to blood vessels, and complications involving the heart. Myocarditis and pericarditis have also been reported after SARS-CoV-2 infection.
This matters when comparing the risks of vaccination and infection. It is not enough to identify a possible vaccine side effect without considering the heart-related risks associated with the disease the vaccine was designed to help prevent.
A CDC analysis using data from 40 U.S. healthcare systems found that the risk of cardiac complications was higher after SARS-CoV-2 infection than after mRNA vaccination across the age and sex groups examined. The analysis covered data from January 2021 to January 2022 and included myocarditis, pericarditis, and other cardiac outcomes.
A large study published in Nature Medicine, using data from England, also compared myocarditis risk after vaccination and after a positive SARS-CoV-2 test. It found that the risk varied by age, sex, and vaccine dose. Although certain groups of younger men had an increased risk after a second dose of Moderna, the overall study found that myocarditis risk was higher after infection than after vaccination in most comparisons.
These studies do not mean that every person faces the same risk or that vaccination decisions can be reduced to a single number. They show why the full comparison matters.
A balanced assessment must consider:
-
The risk of myocarditis after a particular vaccine and dose.
-
The person's age, sex, medical history, and underlying health conditions.
-
The risk of severe COVID-19 illness.
-
The possibility of heart-related complications following infection.
-
The vaccine formulation and recommendations that apply at the time.
A headline that mentions only vaccine-associated myocarditis gives readers an incomplete picture if it does not also explain the cardiovascular risks of COVID-19 itself.